Can eating too much gluten cause celiac disease? What genes, trials and cohort studies show
Short answer
NIDDK says research suggests celiac disease only occurs in people who have certain genes and eat gluten, and that not every carrier of the gene variants who eats gluten develops it1, 2. In genetically at-risk children, observational studies link higher early gluten intake to higher risk3, 38, while two randomized trials did not find that when gluten started changed the rate of disease by 3 to 5 years of age4, 5. The studies we read followed infants and young children; none measured how much gluten an adult eats.
Part of Celiac genetics and family risk, 15 guides

Key points
- Gluten is required, but it is not enough: NIDDK says research suggests celiac disease only occurs in people with certain genes who eat gluten, and not all carriers of DQ2 or DQ8 who eat gluten develop it1, 2.
- NIDDK reports that about 30 percent of people have DQ2 or DQ8 and only about 3 percent of them develop celiac disease6.
- Two randomized trials in infants at higher risk did not find that when gluten started changed the rate of disease by 3 to 5 years of age4, 5. In CELIPREV, more children had celiac disease at 2 years after gluten at 6 months than at 12 months, a difference no longer significant at 5 years5.
- In observational studies of at-risk children, higher gluten intake in early childhood was associated with higher risk, but ESPGHAN says the optimal amounts are undetermined and calls any recommendation on the amount currently unjustifiable3, 38, 7, 8.
- Every trial and cohort study described here followed infants or young children; none we read measured how much gluten an adult eats.
What has to be in place for celiac disease
NIDDK says research suggests that celiac disease only occurs in people who have certain genes and eat food that contains gluten1. Gluten is therefore required, but it is not enough on its own: NIDDK adds that not all people who have the gene variants DQ2 or DQ8 and eat gluten develop the disease2.
The American College of Gastroenterology’s 2023 guideline defines celiac disease as a permanent immune-mediated response to gluten present in wheat, barley and rye9. Gluten is common in foods such as bread, pasta, cookies and cakes10.
The genetic part is narrow. Celiac disease almost always occurs in people who have one of two groups of gene variants, called DQ2 and DQ8, and people without them are very unlikely to develop it11. A 2016 position paper from the European Society for Paediatric Gastroenterology, Hepatology and Nutrition (ESPGHAN) states that the risk of inducing celiac disease through a gluten-containing diet applies exclusively to people carrying at least one of the risk alleles12.
How many people with the genes get celiac disease?
These are NIDDK’s figures. Each comes from its own sentence, and we have not combined them.
| Group | NIDDK’s figure |
|---|---|
| People who have DQ2 or DQ8 | About 30 percent of people6 |
| People with DQ2 or DQ8 who develop celiac disease | Only about 3 percent6 |
| People around the world with celiac disease | Experts estimate about 1 percent13 |
By NIDDK’s numbers, carrying the genes is far more common than having the disease6, 13, so the genes alone do not explain who develops it2. NIDDK says researchers are studying other genes that may increase the chance in people who have DQ2 or DQ814.
What the two infant-feeding trials tested and found
Two randomized trials gave gluten at different times to infants who had a family member with celiac disease. What they compared was when gluten was introduced: 100 mg of gluten a day at 16 to 24 weeks against placebo in one, introduction at 6 months against 12 months in the other15, 16. The abstracts we read do not describe a comparison of a high gluten intake with a low one.
| Trial | Children | What was compared |
|---|---|---|
| PreventCD: multicenter, randomized, double-blind, placebo-controlled15 | 944 children positive for HLA-DQ2 or HLA-DQ8 with at least one first-degree relative with celiac disease15 | 100 mg of gluten a day from 16 to 24 weeks of age, against placebo15 |
| CELIPREV: random assignment16 | 832 newborns with a first-degree relative with celiac disease16 | Gluten introduced at 6 months or at 12 months16 |
PreventCD: a small daily dose from 16 to 24 weeks
At 3 years of age the cumulative incidence of celiac disease was 5.2%, with similar rates in the gluten group (5.9%) and the placebo group (4.5%); the hazard ratio in the gluten group was 1.23 (95% CI 0.79 to 1.91)17. The authors concluded that small quantities of gluten at 16 to 24 weeks of age did not reduce the risk of celiac disease by 3 years of age in this group of high-risk children4.
CELIPREV: gluten at 6 months or at 12 months
At 2 years of age, more children in the 6-month group had celiac disease autoimmunity (16% against 7%) and overt celiac disease (12% against 5%) than in the 12-month group. By 5 years the differences were no longer significant: autoimmunity in 21% and 20% of the two groups, overt disease in 16% and 16%5.
At 10 years, celiac disease autoimmunity was 38% in children with high-risk HLA and 19% in those with standard-risk HLA, and overt celiac disease was 26% against 16%18. The authors concluded that neither delayed introduction of gluten nor breast-feeding modified the risk among at-risk infants, although later introduction was associated with a delayed onset of disease19.
Not every child stayed in CELIPREV: of the 707 participants who remained at 36 months, 553 had a standard-risk or high-risk HLA genotype and completed the study20.
What the observational cohorts found
TEDDY is a prospective observational birth cohort designed to identify environmental triggers of type 1 diabetes and celiac disease. It enrolled 8676 newborns carrying HLA genotypes associated with both conditions21. The researchers did not assign gluten amounts: they estimated intake from three-day food records collected from 6 months to 5 years of age22.
Celiac disease autoimmunity meant positive tissue transglutaminase antibodies in two consecutive blood samples; celiac disease meant biopsy-confirmed disease or persistently high antibody levels23. Of 6605 children with intake data, 18% developed autoimmunity and 7% developed celiac disease24.
Every additional gram of gluten a day was associated with a higher risk of celiac disease, with a hazard ratio of 1.50 (95% CI 1.35 to 1.66)25. The authors concluded that higher gluten intake during the first 5 years of life was associated with increased risk of celiac disease autoimmunity and celiac disease among genetically predisposed children3.
This is the paper cited for NIDDK’s statement that children with a genetic predisposition who eat more gluten in early childhood may have a greater risk26, 27.
TEDDY’s Swedish children: which foods
A later analysis followed 2088 Swedish genetically at-risk children and looked at which gluten sources they ate up to age 228. A high daily bread intake (more than 18.3 g) at 12 months was associated with increased risk of autoimmunity (hazard ratio 1.47, 95% CI 1.05 to 2.05) and of celiac disease (1.79, 95% CI 1.10 to 2.91), compared with no intake29.
Porridge at 9 months (up to 158 g a day, against none) was associated with increased risk of autoimmunity (hazard ratio 1.53, 95% CI 1.05 to 2.23)30. At 18 months, milk cereal drink was associated with increased risk of celiac disease (hazard ratio 1.16 per extra 200 g a day, 95% CI 1.00 to 1.33), and no association was found for other gluten sources up to 24 months31.
Both TEDDY papers report associations from an observational cohort study21, 28.
What the reviews and guidelines conclude
Systematic reviews
For the population at genetic risk, a systematic review updated in 2022 found that age at gluten introduction was not associated with cumulative celiac disease risk, although two randomized trials suggested earlier introduction was associated with earlier appearance of autoimmunity32, 45. It reported that evidence from six observational studies suggests a higher amount of gluten at weaning or afterwards may increase risk, and that there is insufficient evidence to determine the amount associated with increased risk33.
An earlier meta-analysis reported a different pattern for late introduction: a 25% increase in celiac disease risk with late (after 6 months) against recommended (4 to 6 months) gluten introduction, with a risk ratio of 1.25 (95% CI 1.08 to 1.45)34. Its authors found no evidence that early introduction increases risk, and said more studies were needed that control for confounders and evaluate environmental factors in low-risk families35.
ESPGHAN position papers
ESPGHAN’s 2024 update says that introducing gluten at any time between completed 4 months and 12 months of age does not affect the cumulative incidence of celiac disease, although earlier introduction may lead to earlier seroconversion and disease36. It also says breastfeeding, in any amount or of any duration, does not reduce the risk37.
On amounts, the paper summarizes observational cohorts in which consuming a high amount of gluten compared to a low amount during weaning and the first 2 to 3 years, and up to 5 years in some studies, was associated with increased risk38. It then says the specific optimal amounts remain undetermined7, that the impact of restricting gluten in healthy children of unknown risk is unknown39, and that any recommendation on the gluten amount is currently unjustifiable for the general population and for infants with known HLA risk types8.
The 2016 paper had been more specific. Based on observational data, it advised that large quantities of gluten be avoided in the first weeks after introduction and during infancy, and it added that optimal amounts had not been established40. The 2024 paper describes its statements as essentially similar to the 2016 recommendations41, yet on amounts it says any recommendation is currently unjustifiable8. The two papers word the amount question differently.
What do these studies say about adults who eat a lot of bread or pasta?
Every trial and cohort study described on this page followed infants or young children, and each enrolled children chosen for family or genetic risk. The PreventCD and CELIPREV children had a first-degree relative with celiac disease15, 16, and the TEDDY children carried HLA genotypes associated with celiac disease and type 1 diabetes21.
None of the studies we read measured how much gluten an adult eats, so they cannot tell us whether adult intake changes anyone’s risk. NIDDK says celiac disease affects children and adults42.
For parents, the trials asked about timing rather than amount15, 16. ESPGHAN’s 2024 position on both is summarized above36, 8.
This page reports what studies and guidelines say. It is not feeding advice for a particular child.
Where the evidence is still open
- The amount. ESPGHAN says the optimal amounts of gluten are undetermined7, and the 2022 systematic review found insufficient evidence to determine the amount associated with increased risk33.
- Restriction. ESPGHAN says the impact of restricting gluten in healthy children of unknown risk is unknown39.
- Timing against amount. The trials varied when gluten started15, 16, while the cohorts compared amounts eaten22, 28. The 2022 review reports no association between age at introduction and cumulative risk32, and cites evidence from six observational studies for an amount effect33.
- Genes and feeding together. The 2022 review found inconsistent results on whether infant feeding practices change the risk that different HLA genotypes carry43.
- Other triggers. NIDDK says researchers are studying other factors, including a higher number of early infections, certain digestive tract infections and changes in the gut microbiome44.
- Low-risk children. The 2016 meta-analysis called for studies that control for confounders and evaluate environmental factors in low-risk families35.
Verdicts in this guide
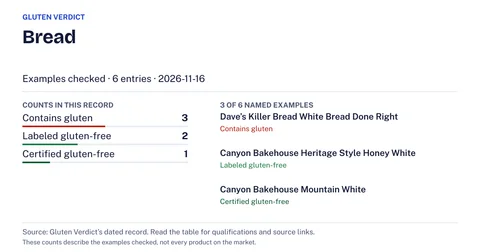
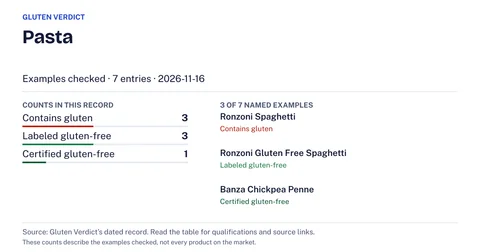
Questions people ask
Can someone develop celiac disease as an adult after years of eating gluten?
NIDDK says celiac disease affects children and adults42. It also says researchers are studying other factors that may increase a person’s chances, such as early infections and changes in the gut microbiome44, and that not every person with the gene variants who eats gluten develops the disease2.
More in Celiac genetics and family risk
 Celiac disease genes beyond HLA: what large genetic studies foundWhat large genetic studies found beyond HLA in celiac disease, how much of the inherited risk those regions explain, and whether clinical tests cover them.
 Is celiac disease hereditary? What runs in families and what does notWhat NIDDK and pooled studies report on inherited risk for celiac disease: the DQ2 and DQ8 genes, twin data, and how rates differ among relatives.
 Carrying a celiac gene: how often it leads to celiac disease and what changes the oddsHow often people with the celiac gene variants develop celiac disease, how a relative with it changes the odds, and what is proven or only suspected.
 Can you develop celiac disease as an adult? What the studies say about late diagnosisWhat NIH, clinical guidelines and studies say about celiac disease found in adulthood, an earlier negative test, delayed diagnosis and testing on gluten.
 MTHFR variants and celiac disease: what studies show about homocysteine and folateWhat four studies found on MTHFR variants in celiac disease, what CDC and ACMG say, and why homocysteine and folate can change at diagnosis.
 What sets off celiac disease? What the evidence says about infections, surgery, pregnancy and stressInfection, surgery, pregnancy and stress are often blamed for celiac disease. Each is graded here by the kind of study behind it and where it stops.
Related guides
 Screening first-degree relatives for celiac disease: who, when and how oftenWhat the ACG, NICE, BSG, ESPGHAN and NIDDK say about testing parents, siblings and children of someone with celiac disease, and how often.
 Does a gluten-free diet change blood sugar? What each study measuredRead the BMJ heart-disease cohort, the type 2 diabetes cohort, a pasta glucose trial and celiac and type 1 diabetes sources by what each measured.
 Can someone with celiac disease eat gluten again?What NIDDK, the ACG guideline and studies say about eating gluten again with celiac disease, why feeling well is not healing, and who runs a challenge.
 Bloated after bread or pasta? Why the celiac blood test comes before cutting glutenWhy bloating after bread or pasta cannot name its cause, why celiac blood tests come before a gluten-free diet, and what to ask a clinician.
Sources
- [1, 2, 6, 11, 14, 26, 27, 44] National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), Celiac Disease: Symptoms & Causes, checked Nov 17, 2026.
Read on 2026-11-17: the sentence on early-childhood gluten intake is followed by note 5, and note 5 in the page’s reference list is Andrén Aronsson C, Lee HS, Hård Af Segerstad EM, et al., “Association of gluten intake during the first 5 years of life with incidence of celiac disease autoimmunity and celiac disease among children at increased risk”, JAMA 2019;322(6):514–523.
- [3, 21, 22, 23, 24, 25] JAMA (PubMed), Association of gluten intake during the first 5 years of life with celiac disease autoimmunity and celiac disease among children at increased risk (TEDDY), checked Nov 17, 2026.
- [4, 15, 17] New England Journal of Medicine (PubMed), Randomized feeding intervention in infants at high risk for celiac disease (PreventCD), checked Nov 17, 2026.
- [5, 16, 18, 19, 20] New England Journal of Medicine (PubMed), Introduction of gluten, HLA status, and the risk of celiac disease in children (CELIPREV), checked Nov 17, 2026.
- [7, 8, 36, 37, 38, 39, 41] Journal of Pediatric Gastroenterology and Nutrition (PubMed), Early diet and the risk of coeliac disease. An update 2024 position paper by the ESPGHAN special interest group on coeliac disease, checked Nov 17, 2026.
- [9] American Journal of Gastroenterology (PubMed), American College of Gastroenterology Guidelines Update: Diagnosis and Management of Celiac Disease, checked Nov 17, 2026.
- [10, 13, 42] National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), Definition & Facts for Celiac Disease, checked Nov 17, 2026.
- [12, 40] Journal of Pediatric Gastroenterology and Nutrition (PubMed), Gluten introduction and the risk of coeliac disease: a position paper by ESPGHAN, checked Nov 17, 2026.
- [28, 29, 30, 31] American Journal of Clinical Nutrition (PubMed), Sources of dietary gluten in the first 2 years of life and associations with celiac disease autoimmunity and celiac disease in Swedish genetically predisposed children (TEDDY), checked Nov 17, 2026.
- [32, 33, 43, 45] Alimentary Pharmacology & Therapeutics (PubMed), Systematic review: early feeding practices and the risk of coeliac disease. A 2022 update and revision, checked Nov 17, 2026.
- [34, 35] Journal of Pediatrics (PubMed), Gluten introduction to infant feeding and risk of celiac disease: systematic review and meta-analysis, checked Nov 17, 2026.